Patient Preferences Shape Dialysis Access Research
An international pilot coauthored by LAU’s Dr. Hicham Cheikh Hassan found that patient preferences and delays in fistula surgery could make a larger randomized dialysis-access trial difficult to conduct.
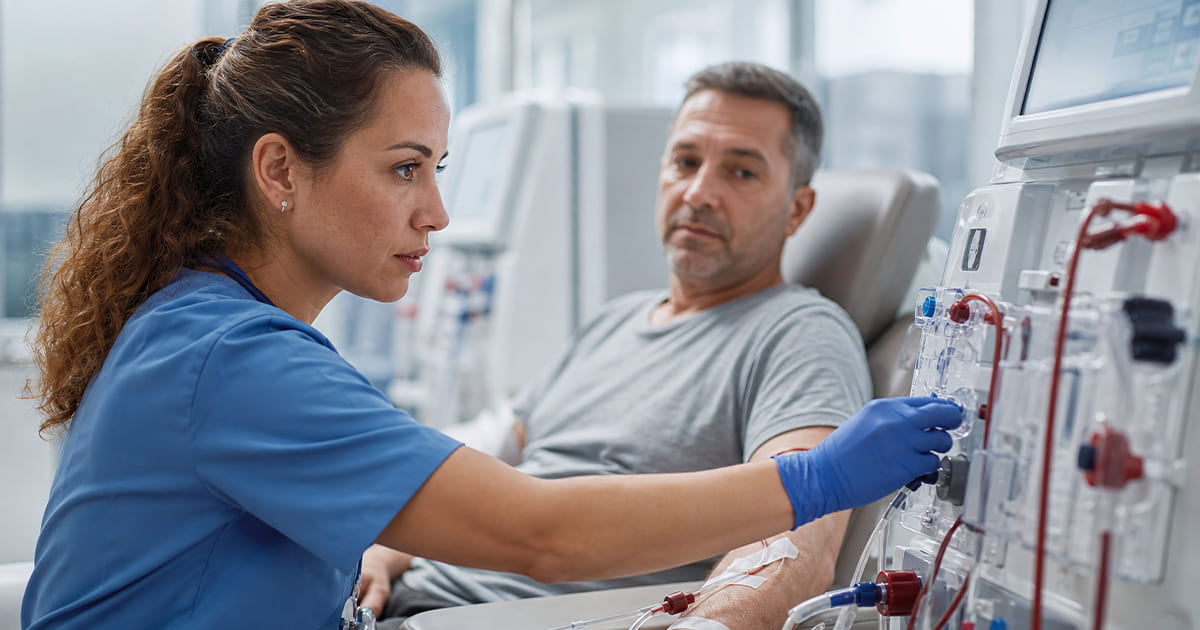
For patients whose kidneys can no longer remove waste and excess fluid from the blood or maintain the body’s delicate balance of salts and minerals, hemodialysis can be life-sustaining. This treatment, which cleans the blood through a dialysis machine, requires reliable access to the bloodstream.
One option is a catheter, a tube placed in a large vein; another is an arteriovenous fistula, created by surgically joining an artery and a vein. The latter has long been preferred, largely because studies have linked its use to better outcomes. But it has not yet been established if the fistula is responsible for this difference, considering that patients who develop a working fistula may be healthier than those who continue with catheters.
For older adults, with limited life expectancy, a fistula may not offer a survival advantage over a catheter as would be expected in younger patients. A randomized trial could help clarify the trade-offs, if enough patients were willing to take part.
That practical question shaped ACCESS HD, a pilot study designed to determine whether a larger randomized trial comparing the two approaches would be feasible. Co-authored by Dr. Hicham Cheikh Hassan, clinical associate professor in the Division of Nephrology at LAU’s Gilbert and Rose-Marie Chagoury School of Medicine, the study titled “Comparing Catheters with Fistulas in Older Patients Starting Hemodialysis: A Pilot Randomized Controlled Trial” was published in the prestigious Journal of the American Society of Nephrology.
As Dr. Cheikh Hassan explained, while there is “no argument that a fistula is superior to a catheter” in younger populations, the clinical equation changes substantially for older individuals. Fistulas in older patients can be problematic: they require an average of 1.5 additional procedures beyond the initial creation surgery to achieve maturation, and with a success rate of around 60 percent, roughly 40 percent never function properly. So, the fundamental question driving the investigation, he added, was whether a fistula makes a difference over a catheter.
The research involved 12 centers in Canada and Australia. Investigators screened 1,287 patients and randomly assigned 67 eligible adults aged 55 or older to either undergo an attempt at creating a fistula or continue with a tunneled catheter. All participants had started hemodialysis through a catheter. The primary measures were willingness to accept random assignment and undergo fistula surgery within 90 days.
The results exposed difficulties in mounting a larger trial. Twenty-five percent of eligible patients accepted randomization, meeting the minimum recruitment proportion specified in the trial registry. The most common reason for declining the procedure was a preference to keep using the existing catheter. In the fistula group, 71 percent underwent surgery within 90 days, below the registered target of at least 80 percent. Considering the findings, the investigators concluded that a definitive trial was not feasible under prevailing conditions, as patient willingness and timely access to surgery were central to that assessment.
Reflecting on the recruitment dynamics, Dr. Cheikh Hassan observed that non-participation was driven by strong, opposing patient preferences: some refused randomization because they viewed a fistula as involving “multiple procedures and interventions which they did not want to be exposed to,” while others were set on getting a fistula in line with standard guidelines and refused to risk placement in the catheter group. “I think what surprised us was that many patients had a catheter, and they wanted to stay on it,” said Dr. Cheikh Hassan. “They did not want to end up being randomized to a fistula creation.”
Addressing why fewer than 80 percent of patients underwent surgery within 90 days, Dr. Cheikh Hassan emphasized that “these are not emergency surgical procedures.” Because most fistulas are planned pre-emptively—often months or even up to a year before dialysis use—and patients typically feel well during their workup, there is no acute clinical urgency.
“I may plan a patient for a fistula in one to two months,” he said, “but until they see the vascular surgeons, have an ultrasound for vein assessment, see the surgeon again, see the anesthetist, have a surgery booked… the non-urgent surgery could be delayed longer than anticipated.”
The fistula group underwent more access-related procedures, required hospitalization, and experienced bloodstream infections that were mostly associated with catheters. Participants who remained on a catheter required medication more often to dissolve clots.
The findings indicate that creating a fistula does not immediately end catheter use, which patients may continue to rely on while awaiting surgery and until the fistula is ready for dialysis. Furthermore, the authors did not identify evidence that assignment to the catheter strategy caused harm. However, with only 67 participants, the study was not designed to determine whether catheters are as safe as, safer than, or less safe than fistulas.
Future studies would need to address patients’ preferences and the steps required to deliver each access strategy. For clinicians and patients, ACCESS HD provides useful evidence about the feasibility of comparing the two approaches, rather than which works better. It supports a careful discussion of treatment options, surgical burden, and uncertainty, with the patient’s priorities explicitly included in the decision.
Ultimately, said Dr. Cheikh Hassan, the pilot answered a crucial question by spotlighting the decisive weight of patient perspective. “We may tell patients that a fistula is better. But in older patients, where a fistula may be associated with more surgeries, they may not see it that way,” he noted, reiterating that active patient involvement in decision-making is essential.
Given these operational barriers, Dr. Cheikh Hassan does not anticipate the trial being repeated anytime soon. “We struggled to have centers include patients in the trial,” he explained, pointing to a persistent divergence in philosophy: “Most centers want a fistula first policy, while most patients want a catheter first approach.” That fundamental friction made recruitment unsustainable.
Nevertheless, clinical guidance is already adapting to these realities. “Whereas before the guideline was ‘fistula first,’ it is now ‘fistula first if it is feasible, if it offers a survival advantage for patients, and if life expectancy justifies it,’” concluded Dr. Cheikh Hassan. “So in elderly patients I anticipate more flexibility when it comes to that option.”
To browse more scholarly output by the LAU community, visit our open-access digital archive, the Lebanese American University Repository (LAUR).


